
Shoulder Labral Tear MRI Signs: SLAP, Bankart, and Instability Review
“Abnormal signal in the labrum” means part of the labrum looks brighter than normal on MRI. It can be a tear, or a normal anatomic variant such as a sublabral recess or a sublabral foramen. Radiologists call it a tear more confidently when contrast or fluid extends into the labrum or the labrum is displaced.
Common Symptoms
- Deep anterior or posterior shoulder pain that is difficult to localize precisely
- Mechanical catching, clicking, or locking sensation during overhead activities
- Sense of instability or the shoulder "slipping" during throwing or reaching motions
- Pain with specific provocative positions such as the cocked arm in overhead athletes
- Decreased throwing velocity or loss of accuracy in overhead athletes
- Aching discomfort at rest that intensifies with activity
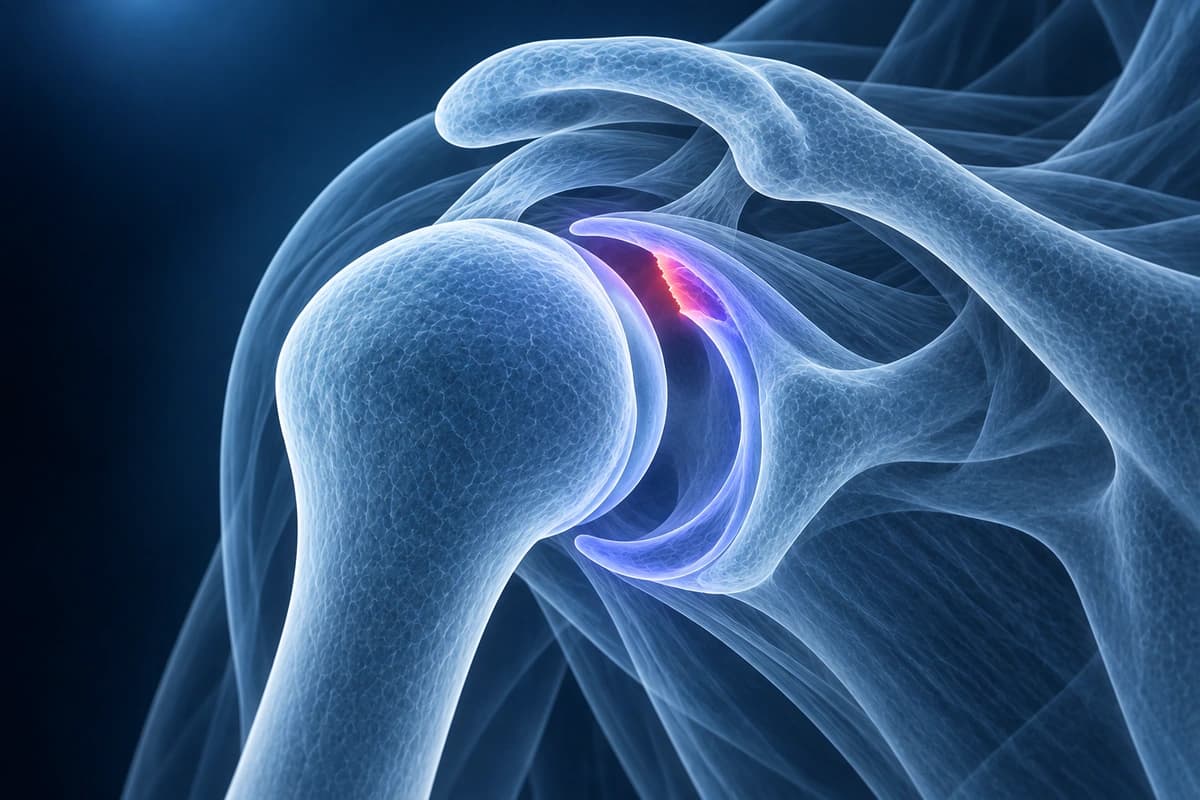
Your report says “abnormal labral signal”: tear or not?
How radiologists phrase it
- “Abnormal signal in the posterior inferior labrum”
- “Increased signal in the superior labrum, sublabral recess versus SLAP tear”
- “Linear signal undercutting the anterior labrum”
- “Sublabral foramen, a normal variant”
Signal, variant or tear
- A sublabral recess is a normal groove under the superior labrum. In a cadaver study it was present in 73% of shoulders and looked much like a SLAP tear.
- A sublabral foramen and a Buford complex are normal variants at the front and top of the labrum that can look detached or missing on MRI.
- Contrast or fluid entering the labrum, an irregular edge or a displaced labral fragment favor a tear, which is then named by location: SLAP at the top, Bankart at the front-bottom, or posterior.
Does the wording change treatment?
Signal alone rarely settles the question; your doctor combines it with any instability, dislocation history and examination. When a standard MRI is uncertain, an MR arthrogram can show the labrum more clearly: in a meta-analysis it detected labral lesions slightly more accurately than MRI.
What to ask at your follow-up
- Is this signal more likely a tear or a normal variant, and where on the labrum is it?
- Does the location fit my symptoms or my dislocation history?
- Would an MR arthrogram or another test change the plan?
Overview
The glenoid labrum is a fibrocartilaginous ring that deepens the shoulder socket and serves as an attachment point for the glenohumeral ligaments and long head of the biceps tendon. Labral tears are classified by location and pattern: SLAP (Superior Labrum Anterior to Posterior) tears involve the superior labrum at the biceps anchor, while Bankart lesions involve the anteroinferior labrum and are associated with shoulder dislocations. This page focuses on the imaging workup: where the labrum is torn, which MRI planes show it best, and whether instability-related bone injuries are also present.
For a deeper guide to superior labrum types, read the SLAP tear classification guide. For dislocation-related labral injury and bone loss, see the Bankart and Hill-Sachs MRI guide.
Key Imaging Findings
- Labral detachment or irregularity on axial or coronal MRI
- SLAP tear with extension into the biceps anchor
- Bankart lesion with anteroinferior labral avulsion
- Bony Bankart with glenoid rim fracture
- Hill-Sachs lesion on the posterolateral humeral head
- Paralabral cyst suggesting underlying labral tear
How MRI Separates SLAP, Bankart, and Posterior Tears
A SLAP lesion is centered at the superior labrum and biceps anchor, so coronal-oblique and axial images are reviewed for fluid undercutting the labrum, detachment of the biceps anchor, or extension into the long head of biceps tendon. These findings explain deep pain with overhead loading, throwing, or traction injuries.
A Bankart lesion sits at the anteroinferior labrum after anterior dislocation. Axial images are checked for labral avulsion, capsulolabral stripping, glenoid rim fracture, and a matching Hill-Sachs impaction injury on the humeral head. Posterior labral tears are assessed separately because they can follow posterior instability or repetitive loading rather than classic anterior dislocation.
Imaging Questions This Page Helps Answer
- Is the tear superior, anterior, posterior, or circumferential around the glenoid?
- Does the abnormal signal extend into the biceps anchor, suggesting a SLAP pattern?
- Is there a Bankart lesion, bony Bankart fragment, or glenoid bone loss after instability?
- Are associated findings present, such as a Hill-Sachs lesion, paralabral cyst, cartilage injury, or rotator cuff tear?
AI Search Quick Answers
- Can MRI show a shoulder labral tear? MRI can show many labral tears, especially when fluid or contrast separates the labrum from the glenoid. MR arthrogram may be better for subtle SLAP, Bankart, or posterior tears.
- Can X-ray diagnose a labral tear? X-ray does not directly show the labrum, but it can show related bone findings such as glenoid rim fracture, Hill-Sachs injury, arthritis, or dislocation alignment.
- When is CT better than MRI? CT is better for glenoid bone loss, bony Bankart fragment size, and fracture detail after instability. MRI is usually better for the labrum, capsule, biceps anchor, cartilage, and rotator cuff.
- What can AI not diagnose? AI cannot confirm shoulder instability, choose surgery, or replace a clinician who compares imaging with symptoms and physical exam.
Review images in the free shoulder MRI viewer or free shoulder CT viewer, then compare related pages for shoulder impingement and clavicle fracture.
Medical Safety and Source Context
Labral tear wording can vary between radiology reports, orthopedic exams, and surgical findings. Treat AI explanations as orientation: they can organize visible imaging clues, but they cannot confirm instability, identify the pain generator, or decide whether therapy, injection, arthroscopy, or urgent evaluation is needed.
Discuss the report with a clinician who can compare symptoms, instability tests, range of motion, strength, prior dislocation history, and whether MRI, MR arthrography, CT, or CT arthrography is the right next study.
Frequently Asked Questions
What is the difference between a SLAP tear and a Bankart lesion?
A SLAP (Superior Labrum Anterior to Posterior) tear involves the superior labrum at the biceps anchor, typically caused by repetitive overhead loading or a fall on an outstretched arm. A Bankart lesion is an anteroinferior labral avulsion at the 3 to 6 o'clock position resulting from anterior glenohumeral dislocation. Both are best visualized on MR arthrogram, where intra-articular gadolinium outlines the labrum and highlights tears as linear contrast extension into the labral tissue. Axial T2-FS images depict Bankart lesions, while coronal-oblique and sagittal sequences demonstrate SLAP tears at the biceps anchor.
How accurate is MR arthrogram for diagnosing labral tears?
MR arthrogram is the most sensitive imaging study for labral pathology, with sensitivity exceeding 90% for SLAP tears and anteroinferior Bankart lesions. Intra-articular gadolinium distends the joint capsule and infiltrates labral defects, converting subtle fraying to clearly demarcated signal abnormalities. Standard MRI without arthrogram misses a significant proportion of partial labral tears. The axial plane is critical for Bankart lesions, while the coronal-oblique plane evaluates the superior labrum and biceps anchor. A Hill-Sachs impaction fracture of the posterosuperior humeral head, visible on axial images, corroborates a history of anterior dislocation.
What are the surgical options for labral tears?
Arthroscopic labral repair is the standard treatment for symptomatic Bankart and SLAP lesions that fail conservative management. For Bankart repairs, the anteroinferior labrum is reattached to the glenoid rim with suture anchors, restoring the labral bumper and capsulolabral complex. SLAP repairs reattach the superior labrum and biceps anchor. In patients over 35 with SLAP tears, biceps tenodesis often produces more reliable results than superior labral repair. Bony Bankart lesions with significant anterior glenoid bone loss may require the Latarjet coracoid transfer procedure to restore osseous stability. Postoperative rehabilitation focuses on progressive range of motion followed by rotator cuff strengthening.
Sources
- Snyder SJ, Karzel RP, Del Pizzo W, et al. SLAP lesions of the shoulder. Arthroscopy. 1990;6(4):274-279.
- Bankart ASB. The pathology and treatment of recurrent dislocation of the shoulder-joint. Br J Surg. 1938;26(101):23-29.
- Hill HA, Sachs MD. The grooved defect of the humeral head. Radiology. 1940;35(6):690-700.
- Woertler K, Waldt S. MR imaging in sports-related glenohumeral instability. Eur Radiol. 2006;16(12):2622-2636.
- Smith DK, Chopp TM, Aufdemorte TB, et al. Sublabral recess of the superior glenoid labrum: study of cadavers with conventional nonenhanced MR imaging, MR arthrography, anatomic dissection, and limited histologic examination. Radiology. 1996;201(1):251-256.
- Tuite MJ, Orwin JF. Anterosuperior labral variants of the shoulder: appearance on gradient-recalled-echo and fast spin-echo MR images. Radiology. 1996;199(2):537-540.
- Mohana-Borges AV, Chung CB, Resnick D. Superior labral anteroposterior tear: classification and diagnosis on MRI and MR arthrography. AJR Am J Roentgenol. 2003;181(6):1449-1462.
- Smith TO, Drew BT, Toms AP. A meta-analysis of the diagnostic test accuracy of MRA and MRI for the detection of glenoid labral injury. Arch Orthop Trauma Surg. 2012;132(7):905-919.
Related Articles
Your doctor ordered a shoulder MR arthrogram, or the report mentions one? Learn why contrast goes into the joint, what it shows better than MRI and what to ask.
Your shoulder MRI mentions a SLAP tear? Learn what types I to IV mean, from labrum fraying to biceps anchor detachment, and how each type is treated.
After a shoulder dislocation, MRI often shows a Bankart tear and a Hill-Sachs lesion. Learn what they mean, why bone loss matters and the risk of recurrence.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer