
Shoulder Impingement MRI Signs: Rotator Cuff & Subacromial Review
These phrases describe the space the rotator cuff passes through. Acromion type 1, 2 or 3 is the shape of the bony roof: flat, curved or hooked. Subacromial narrowing means a reduced acromiohumeral distance. AC joint arthrosis is wear of the nearby joint, and subacromial bursitis is fluid or thickening in the bursa.
Common Symptoms
- Anterolateral shoulder pain that worsens when lifting the arm to the side or forward
- Painful arc of motion classically between 70° and 120° of abduction
- Night pain, particularly when rolling onto the affected shoulder
- Weakness with resisted shoulder elevation or external rotation
- Pain with reaching overhead or behind the back
- Tenderness over the anterior acromion and subacromial space on palpation
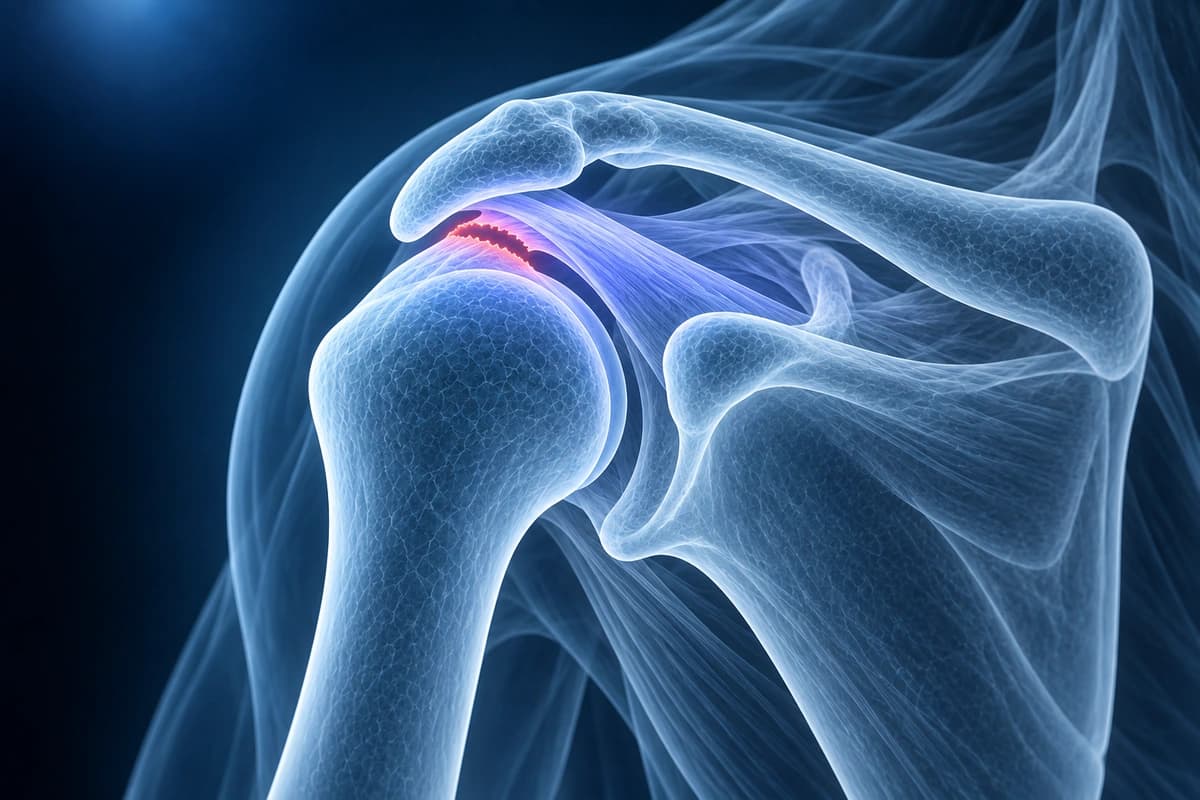
Acromion type, subacromial narrowing and AC joint arthrosis in your report
How radiologists phrase it
- “Type II (curved) acromion” or “type III hooked acromion”
- “Narrowed subacromial space, acromiohumeral distance 6 mm”
- “Hypertrophic AC joint arthrosis with inferior osteophytes”
- “Fluid in the subacromial-subdeltoid bursa, consistent with bursitis”
What the measurements show
- In one MRI study, hooked (type 3) acromions were far more common in shoulders with full-thickness cuff tears (62%) than in control shoulders (13%), so a hooked acromion is not a tear by itself.
- An acromiohumeral distance of 7 mm or less went with full-thickness supraspinatus tears in 90% of patients in one study, and with more fatty change in the cuff muscles.
- In patients with impingement, the distance matched symptoms better than acromion shape, and the two measurements were not related.
- AC joint wear is common on MRI in people without shoulder pain; bone edema around the AC joint was a more reliable sign that the joint itself causes pain.
Does it change the plan?
Bone shape alone is not a diagnosis. Removing part of the acromion was first described for chronic impingement that did not settle, but these findings are judged together with your examination, the state of the rotator cuff and how you respond to rehabilitation.
What to ask at your follow-up
- Is my acromion shape or the narrowed space likely to explain my pain?
- What is my acromiohumeral distance, and is the rotator cuff torn?
- Is there bone edema at the AC joint, or only wear?
- What should I try before any procedure is considered?
Overview
Shoulder impingement syndrome occurs when the rotator cuff tendons and subacromial bursa are compressed during overhead movements. This can result from subacromial narrowing (external impingement) or internal impingement during abduction and external rotation. Imaging evaluates acromion morphology, subacromial space, bursal thickening, and early rotator cuff changes.
Key Imaging Findings
- Subacromial-subdeltoid bursitis with fluid and thickening
- Acromion morphology assessment (Type I flat, Type II curved, Type III hooked)
- Subacromial spur formation narrowing the subacromial space
- Acromioclavicular joint hypertrophy with inferior osteophytes
- Early rotator cuff tendinopathy or partial tear
- Os acromiale contributing to impingement
Related Shoulder Imaging Guides
If your report mentions subacromial narrowing, AC joint hypertrophy, or a hooked acromion, compare the impingement findings with adjacent shoulder MRI and CT guides.
AI Search Quick Answers
Can MRI show shoulder impingement?
MRI can show bursitis, rotator cuff tendinopathy, partial tearing, AC joint osteophytes, and acromion shape that may support an impingement pattern. Imaging does not prove the pain source by itself, so a clinician should match the findings with motion, strength, and exam tests.
Can X-ray diagnose shoulder impingement?
X-ray can show a hooked acromion, AC joint arthritis, calcific tendinitis, or bone alignment issues, but it cannot show the rotator cuff tendon or bursa in detail. MRI or ultrasound is usually needed when soft-tissue injury is the main question.
What should a clinician confirm?
A clinician should confirm whether symptoms come from impingement, rotator cuff tear, stiffness, neck referral, labral injury, or arthritis. Treatment decisions depend on pain pattern, function, duration, exam findings, and response to therapy.
What can AI not diagnose?
AI cannot determine the true pain generator, grade weakness on exam, or decide whether injection, therapy, or surgery is appropriate. Use AI findings as educational context for a radiologist, physical therapist, or orthopedic clinician.
Frequently Asked Questions
What causes shoulder impingement syndrome?
Shoulder impingement results from mechanical compression of the supraspinatus tendon and subacromial bursa between the humeral head and the coracoacromial arch during arm elevation. Primary impingement is caused by structural narrowing — a hooked (type III) acromion, os acromiale, or hypertrophic acromioclavicular joint — that reduces the subacromial space below its normal 7–10 mm. Secondary impingement occurs when rotator cuff weakness, glenohumeral instability, or scapular dyskinesia causes dynamic superior migration of the humeral head. Repetitive overhead activities in athletes and manual laborers accelerate subacromial bursal thickening and tendinopathic change in the supraspinatus critical zone.
How does MRI differentiate impingement from a rotator cuff tear?
On MRI, subacromial impingement without a tear demonstrates subacromial-subdeltoid bursal thickening and fluid, peritendinous edema, and increased signal within the supraspinatus on T2-weighted fat-suppressed images without a discrete through-and-through defect. Coronal-oblique T2-FS sequences are the primary plane for evaluating the supraspinatus tendon. A hooked acromion or inferior acromioclavicular osteophytes narrowing the subacromial space are visible on sagittal images. Full-thickness rotator cuff tears are distinguished by fluid signal traversing the entire tendon thickness. Axial T2-FS images complement coronal sequences by evaluating the subscapularis and long head of the biceps tendon.
What is the first-line treatment for shoulder impingement?
Conservative management successfully resolves symptoms in the majority of patients with impingement syndrome. Physical therapy targeting posterior capsule stretching, rotator cuff strengthening, and scapular stabilization is the cornerstone of treatment. NSAIDs and a subacromial corticosteroid injection provide short-term pain relief to facilitate rehabilitation. Activity modification to avoid provocative overhead postures is essential. Surgical intervention — arthroscopic subacromial decompression with acromioplasty — is reserved for patients with persistent symptoms after at least 3–6 months of dedicated conservative therapy. Concomitant rotator cuff pathology identified on MRI or at arthroscopy is addressed at the same operative setting.
Sources
- Epstein RE, Schweitzer ME, Frieman BG, et al. Hooked acromion: prevalence on MR images of painful shoulders. Radiology. 1993;187(2):479-481.
- Saupe N, Pfirrmann CW, Schmid MR, et al. Association between rotator cuff abnormalities and reduced acromiohumeral distance. AJR Am J Roentgenol. 2006;187(2):376-382.
- Mayerhoefer ME, Breitenseher MJ, Wurnig C, Roposch A. Shoulder impingement: relationship of clinical symptoms and imaging criteria. Clin J Sport Med. 2009;19(2):83-89.
- Shubin Stein BE, Ahmad CS, Pfaff CH, et al. A comparison of magnetic resonance imaging findings of the acromioclavicular joint in symptomatic versus asymptomatic patients. J Shoulder Elbow Surg. 2006;15(1):56-59.
- Neer CS 2nd. Anterior acromioplasty for the chronic impingement syndrome in the shoulder: a preliminary report. J Bone Joint Surg Am. 1972;54(1):41-50.
Related Articles
Explore whether rotator cuff tears can heal conservatively, factors affecting recovery, and when surgery becomes necessary.
Evidence-based rotator cuff rehabilitation exercises, phases of recovery, and tips for optimal shoulder healing.
Your MRI says partial- or full-thickness rotator cuff tear? Learn what these terms, tear size and retraction mean, and how they shape treatment choices.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer