
Clavicle Fracture X-ray & CT Signs: Shoulder Injury Review
Clavicle fractures are the most common shoulder girdle fracture, accounting for approximately 5% of all adult fractures. The middle third of the clavicle is involved in roughly 80% of cases due to its thin cross-section and lack of muscular or ligamentous support. Lateral third fractures account for 15% and medial third for 5%. Imaging is critical for characterizing fracture pattern, displacement, comminution, and shortening, all of which influence treatment decisions. AI can help explain fracture terms, but a clinician must confirm the findings and decide how the fracture should be managed.
Common Symptoms
- Immediate sharp pain at the clavicle following a fall on the shoulder or outstretched hand
- Visible or palpable deformity, tenting of the skin, or bony crepitus over the fracture site
- The arm held close to the body with the head tilted toward the injured side to relieve tension
- Swelling and bruising along the clavicle that develops over hours
- Painful restriction of arm movement, particularly elevation above shoulder height
- Neurovascular symptoms including numbness or hand weakness if the brachial plexus or subclavian vessels are compressed
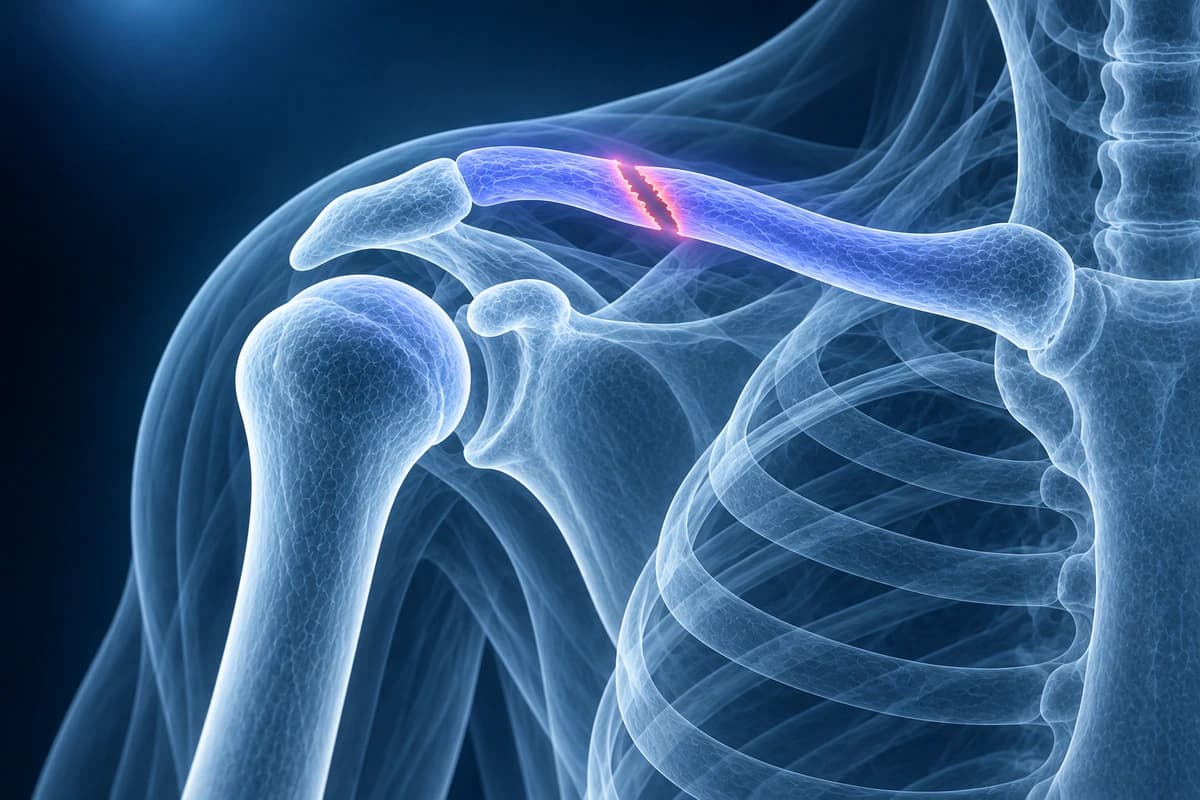
What We Look For on Imaging
- Fracture line location classified as medial, middle, or lateral third
- Degree of displacement and angulation between fracture fragments
- Comminution indicating higher-energy injury with multiple fragments
- Clavicular shortening exceeding 2 cm, which may favor surgical fixation
- Proximity of fragments to subclavian vessels and brachial plexus
- Associated injuries including pneumothorax, rib fractures, or AC joint disruption
Review Clavicle CT and Adjacent Shoulder Injuries
CT can clarify medial or complex clavicle fractures, sternoclavicular alignment, and comminution when X-ray views are limited. Use these current-domain guides to compare related shoulder girdle findings.
AI Search Quick Answers
Can X-ray diagnose a clavicle fracture?
X-ray is usually the first test and can show most clavicle fractures, displacement, angulation, and shortening. A clinician still needs to assess skin tenting, neurovascular status, pain, and whether the fracture pattern is stable.
When is CT better for a clavicle fracture?
CT is better for medial clavicle fractures, sternoclavicular joint alignment, complex comminution, intra-articular extension, and surgical planning when standard X-ray views do not answer the question clearly.
Can MRI show a clavicle fracture?
MRI can show marrow edema and soft-tissue injuries around the shoulder, but it is not usually the main test for clavicle fracture alignment. MRI is more useful when labrum, rotator cuff, AC ligament, or occult stress injury is also suspected.
What can AI not diagnose?
AI cannot determine skin risk, nerve or vessel injury, safe return to sport, or whether surgery is required. It can summarize visible imaging clues, but urgent symptoms and treatment choices need clinician review.
Frequently Asked Questions
How are clavicle fractures classified and does location affect treatment?
Clavicle fractures are classified by location: group I (midshaft, 80% of fractures), group II (distal third, 15%), and group III (medial third, 5%). Midshaft fractures are further described by Robinson's classification based on displacement and comminution. Distal clavicle fractures are subclassified by Neer type: type I (lateral to CC ligaments, stable), type II (medial to CC ligaments, unstable due to CC ligament disruption), and type III (intra-articular). Plain radiographs with AP and 15° cephalic tilt (Zanca view) for the AC joint are the primary imaging modality. CT adds value for complex fractures, medial physeal injuries in adolescents, and neurovascular evaluation. MRI is reserved for suspected concurrent soft-tissue shoulder injury.
When is surgical fixation recommended for a clavicle fracture?
Absolute indications for surgical fixation include open fractures, impending skin perforation, neurovascular compromise, and floating shoulder (concurrent ipsilateral clavicle and scapular neck fractures). Relative indications for operative treatment of displaced midshaft fractures include shortening greater than 15–20 mm, complete displacement (no cortical contact), comminution, and high-demand overhead athletes. Meta-analyses demonstrate higher union rates and faster return to activity with plate fixation compared to nonoperative management for displaced midshaft fractures, at the cost of hardware-related complications requiring plate removal in up to 30% of cases. Unstable Neer type II distal clavicle fractures with CC ligament disruption are reliably treated surgically given high nonunion rates with conservative care.
What complications can arise after a clavicle fracture?
Nonunion occurs in approximately 1–5% of midshaft fractures treated conservatively, rising to 15% for displaced fractures with significant shortening. Symptomatic nonunion requires surgical debridement, plate fixation, and bone grafting. Malunion with clavicular shortening greater than 15 mm causes scapular protraction, altered glenohumeral biomechanics, and shoulder weakness. Post-traumatic thoracic outlet syndrome can arise from callus formation or malunion compressing the brachial plexus or subclavian vessels, producing neurogenic symptoms in the arm and hand. The axillary nerve and brachial plexus are at risk from fracture displacement or hematoma. Delayed AC joint arthritis may follow distal clavicle fractures that heal in malposition or with intra-articular extension.
Sources
- Robinson CM. Fractures of the clavicle in the adult. Epidemiology and classification. J Bone Joint Surg Br. 1998;80(3):476-484.
- Zlowodzki M, Zelle BA, Cole PA, et al. Treatment of acute midshaft clavicle fractures: systematic review of 2144 fractures: on behalf of the Evidence-Based Orthopaedic Trauma Working Group. J Orthop Trauma. 2005;19(7):504-507.
- Canadian Orthopaedic Trauma Society. Nonoperative treatment compared with plate fixation of displaced midshaft clavicular fractures. A multicenter, randomized clinical trial. J Bone Joint Surg Am. 2007;89(1):1-10.
- McKee RC, Whelan DB, Schemitsch EH, McKee MD. Operative versus nonoperative care of displaced midshaft clavicular fractures: a meta-analysis of randomized clinical trials. J Bone Joint Surg Am. 2012;94(8):675-684.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer